

A schedule with gaps is rarely, first of all, an acquisition problem — it's a leak problem: patients who already exist and get lost along the way. Before spending more on marketing, count one week's gaps and give each a cause (late cancellation, no-show, unbooked recall, inactive patient, out-of-hours demand), because each one has a different fix. The arithmetic with your own numbers: 14 gaps × €90 average visit value = €1,260 a week, around €5,000 a month that was already in your schedule.
"How to fill my dental clinic schedule" is a search that almost always ends in the same answer: spend more on marketing. Ads, social media, booking portals. Before accepting it, do a shorter piece of maths. Go back over last week's schedule and count the gaps that were never filled. If you find 14 gaps and your average visit value is €90, that week cost you 14 × €90 = €1,260 in chair time you had already paid for. Over a month, around €5,000.
Almost none of that is fixed by more advertising, because almost none of it is a lack of demand. In 2026, what empties most established schedules is not a shortage of new patients but leaks: patients who already exist and get lost along the way. Cancelled appointments nobody refills, patients who don't show up, check-ups that never get booked, inactive patients nobody brings back.
This article proposes working in a different order. First, diagnose where your gaps come from. Then close each leak with the fix that matches it. And leave marketing for the end, once the schedule holds on to what comes in.
Why "more marketing" is rarely the first answer
Most content about how to fill a dental clinic schedule talks about acquisition: campaigns, social media, influencer collaborations, portals. That's understandable — the people writing those guides usually sell marketing — but it leaves out half the problem, and it tends to be the bigger half.
Investing in acquisition while your schedule loses appointments is pouring water into a leaky bucket. New water comes in at the top and escapes at the bottom. And the new water is the expensive kind: a new patient costs ads, first-visit time and trust that doesn't exist yet. A patient who already knows you costs one WhatsApp message.
"The schedule has too many gaps and I couldn't tell you where they come from." It's the sentence we hear most often from clinic managers when this topic comes up (we quote it as a pattern from our sales conversations, not as one person's literal words). The second half of the sentence is the real problem: without knowing where the gaps come from, any solution is a blind bet.
It's worth saying the reverse too: this is not an argument against marketing. It's an argument about order. The case where acquisition genuinely comes first is further down.
Before filling the schedule: find out where the gaps come from
The diagnosis needs no consultancy and no software. It needs one week and a notebook.
- Every day, at closing time, write down the gaps. Count every slot of 30 minutes or more that stayed empty on an operating chair.
- Assign each one a cause. Five categories cover almost everything: a late cancellation nobody refilled, a no-show, a check-up that never got booked, an inactive patient nobody brought back, and a structural gap (an hour simply nobody asked for).
- Separate the avoidable from the unavoidable. Last-minute flu will always exist. The useful question is not "why did they cancel?" but "did anyone try to refill the slot?".
- On Friday, multiply. Avoidable gaps × average visit value. With 14 gaps at €90: 14 × €90 = €1,260 that week. Over four weeks, about €5,040 a month.
Two caveats to keep the number honest. A schedule at 100% occupancy is not a realistic target, and not every gap is worth exactly the average: some slots are €40 check-ups, others €400 root canals. The exercise is not after accounting precision. It's after something more useful: knowing what share of your gaps has an identifiable cause and a known fix. In most schedules we review with clinics, it's the majority.
That number also gives you a benchmark for decisions. If your avoidable gaps add up to €5,000 a month, you know how much you can justify spending to close them — and what to compare any marketing budget against.
The five leaks in a dental schedule and how each one closes
Each cause has a different fix, and applying the wrong one doesn't move the number: more reminders won't fix recall that never happens, and more ads won't fix anything on this list. Each fix has its own guide on this blog; here is the map.
1. Late cancellations nobody refills
A patient cancels Wednesday's 9:00 appointment on Tuesday at 16:00. The front desk notes it down, keeps handling the counter and the phone, and the slot dies right there: nobody has twenty minutes to call ten patients and ask if one of them can come in tomorrow morning.
The fix is a waiting list that works on its own: when a slot opens up, the system offers that time over WhatsApp to compatible patients and the first to accept takes it, without the front desk dialling a single number. We explain this layer in detail in how to reduce no-shows at your dental clinic.
2. Silent no-shows
Worse than a cancellation, because there's no warning: the patient simply doesn't turn up, and those 45 minutes are gone for good. The defence is not penalties but making it easy to respond: WhatsApp reminders where confirming, rescheduling or cancelling takes one tap.
The counterintuitive idea, developed in the same no-show guide: you want cancelling to be easy. A cancellation with notice is a slot the waiting list can recover; a no-show is a slot lost for certain.
3. Check-ups that never get booked (the recall that slips away)
The patient finishes treatment, leaves without a next appointment, and the "we'll call you about your check-up" never happens — not out of neglect, but because it depends on someone finding a free hour to pull lists from the practice software and start dialling. Every unbooked check-up is an invisible gap: it never existed in the schedule, so nobody counts it as a loss.
It's demand you had already earned. The fix is automated dental recall that contacts each patient when they're due, without depending on anyone's memory or spare time.
4. Inactive patients nobody brings back
The highest-volume leak. Ask your practice software for the list of patients with no visit in the last 12 months and multiply by your average treatment value: 1,000 inactive patients × €110 = €110,000 of pending treatment sitting outside your schedule. Not all of them would come back even if you contacted every one — some have moved, others no longer need it — but it's the biggest pool of demand you have, and it already knows you.
Recovering it by hand doesn't fit into anyone's day: 1,000 calls × 5 minutes is more than 80 hours. That's why how to reactivate inactive patients is the most important step-by-step guide on this list, and you can size your own case with the reactivation calculator.
5. Out-of-hours demand that never gets in
Your clinic is open around 50 of the week's 168 hours: 70% of the time, nobody answers. The patient writing at 21:30 to ask whether you take their insurance doesn't usually wait until tomorrow: they also write to another clinic, and they stay with the one that replies.
These gaps never show up in the audit — they never became appointments — but they close the same way: with 24/7 online appointment booking. The patient sorts out their questions over WhatsApp and receives a calendar link where they pick their own time; the appointment lands written in your schedule.
Where to start: the order that recovers the most for the least
Try to fix all five leaks at once and you'll fix none. Our recommended order, from fastest return to deepest:
- Reminders with a response, plus the waiting list. They protect the appointments you already have, work from week one, and depend little on the quality of your database.
- Recall. Demand already earned: patients who finished treatment and are due a check-up. Steady volume, month after month.
- Reactivating inactive patients. The biggest pool, but it needs a contactable database and well-crafted messages; that's why it comes third, not first.
- 24/7 capture. Closes the door that new demand was already escaping through.
And marketing? At the end, once the bucket holds water. The same acquisition budget performs better when every new appointment lands in a schedule that confirms, refills and recovers.
Each layer can be run by hand, with software your team operates, or with an autonomous system that operates it for you. Dental clinic automation: what to automate and what not has the task-by-task inventory, and how to apply artificial intelligence at your dental clinic gives you the framework for evaluating options.
When the problem really is acquisition
To be honest about the other case. If your clinic opened a few months ago, your database holds a few hundred contactable patients, or you've just added chairs, you don't yet have a pool of inactive patients or recall volume to recover. There, acquisition genuinely comes first, and the pieces that help it most are Google reviews and online booking that turns interest into appointments.
Even then, set up reminders first: there is no worse investment than paying to attract a new patient and losing them to a no-show at their first visit.
Does this work with my practice management software?
It's the question we get asked most, and the short answer is yes. An autonomous system like Keishal integrates with the software you already use — Gesden, Nubimed, Dentalink, Clinic Cloud, Flowww, Klinikare and others — with no migration: it reads your current schedule and database and writes appointments, confirmations and status changes back into them. Your team learns no new tool; they see the results in the same program they use today.
Start by counting, not buying
This week, count your gaps and give each one a cause. It's one hour of work spread over five days, and it turns "I need more patients" into something much cheaper to solve: "I need to recover the ones I already have".
If you want to size the biggest leak, the reactivation calculator gives you the number from your own database in a minute. And if you'd rather see all of this running for a clinic like yours, book a demo.

Ready to try Keishal in your dental clinic?
Book a demo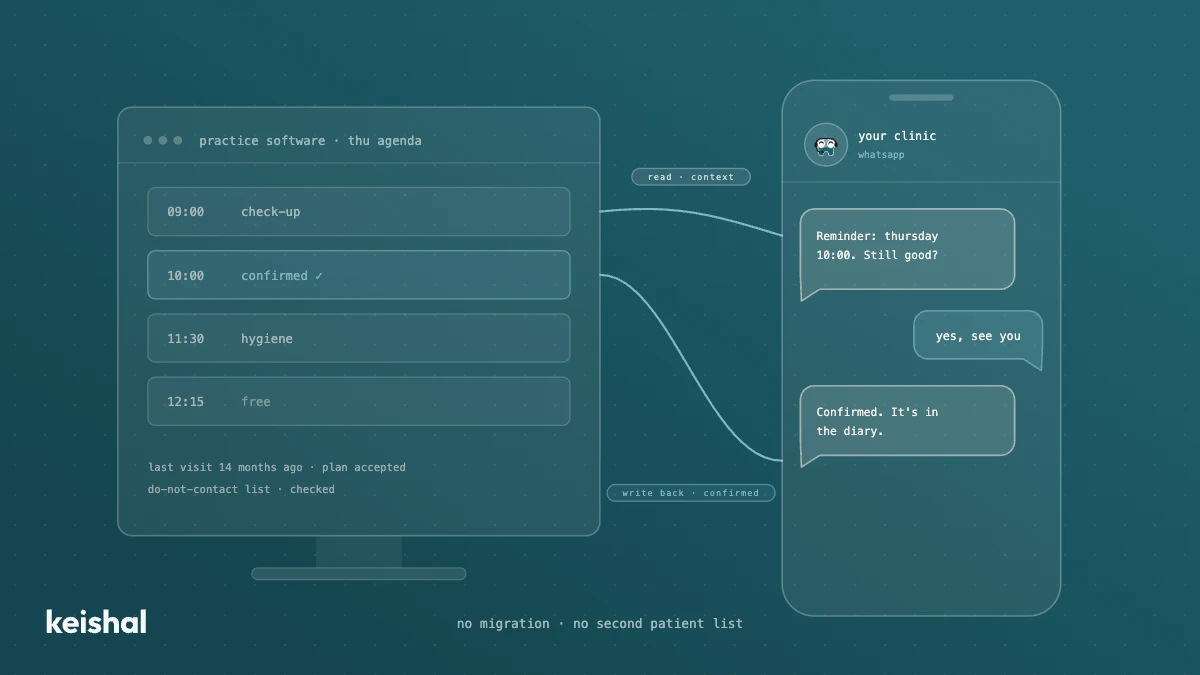
Integrating AI with your dental practice software: what a real connection means
A real integration with your dental clinic's software does two jobs: it reads your patients' data for context and writes appointments, confirmations and status changes back into your program. A monthly CSV, a calendar connector or a read-only tool leaves the rest to your team: with 330 reminders a month, marking each confirmation at 30 seconds adds up to almost 3 hours. Ask for the list of supported programs and versions in writing, and check that there's no migration and no duplicate patient base.
Switching dental software: what migrating really involves and when you don't need to
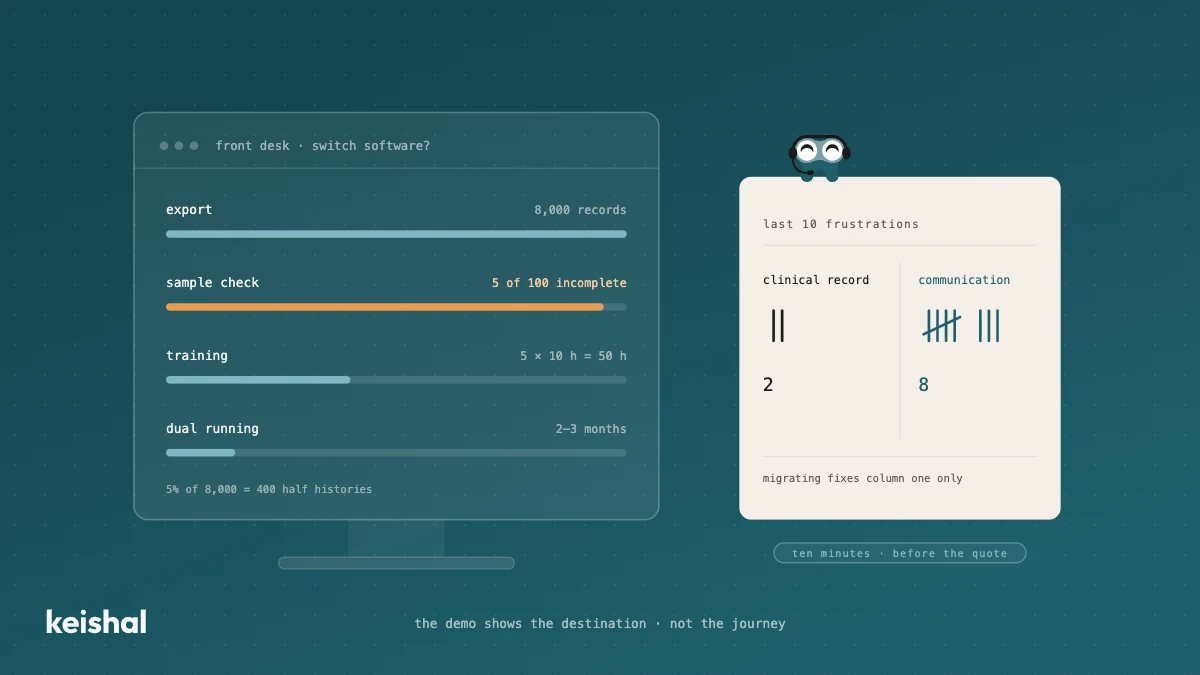
Switching dental software isn't installing a program: it's exporting and verifying thousands of records, training the team (5 people × 10 hours = 50 hours) and running two systems side by side for two or three months. It's worth it when the software has no support, holds your data hostage or the clinic has outgrown it. But if what's pushing you is unmanaged reminders, recall that never happens and out-of-hours messages, that communication layer can be added on top of your current PMS, without migrating anything.